
 By admin
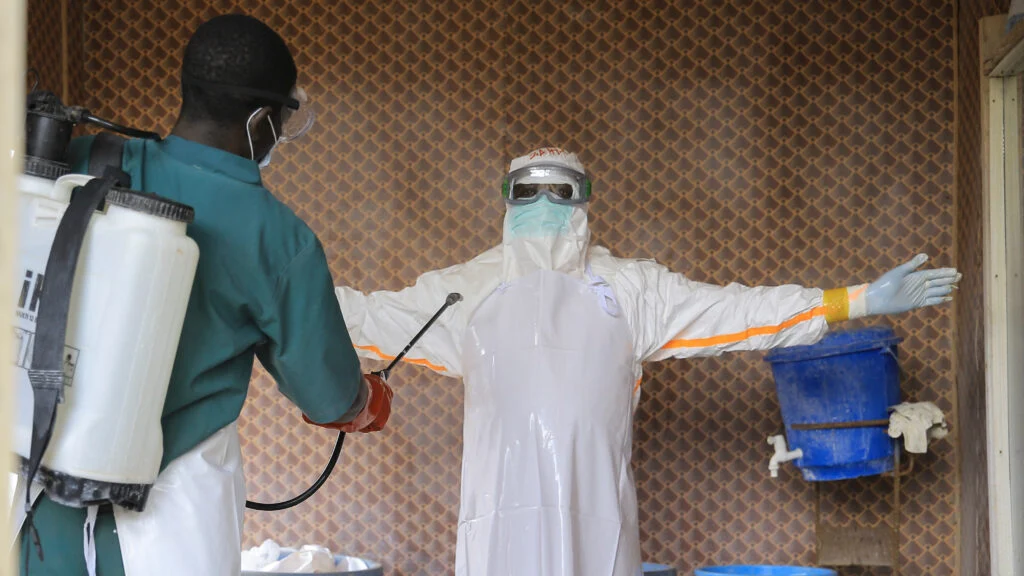
The Democratic Republic of the Congo (DRC) has reached a harrowing milestone in its battle against one of the world’s most lethal pathogens. Health authorities confirmed on Thursday that the death toll from the ongoing Ebola virus disease (EVD) outbreak has surpassed 4,000, cementing this crisis as the fastest-growing Ebola epidemic in history. According to the latest data released by the Congolese Ministry of Health, there have been 4,018 deaths among 8,300 recorded cases since the outbreak was officially declared on May 15 in the volatile eastern provinces of the country. This surge in mortality and infection comes at a precarious moment when the response infrastructure is being systematically dismantled by a combination of labor unrest, military aggression, and deep-seated community mistrust.
The epicenter of the current crisis is Ituri Province, where the humanitarian situation has taken a sharp turn for the worse. While the medical community struggles to treat the infected, the very people tasked with tracking the virus have walked off the job. In Bunia, the provincial capital, health workers—including members of critical surveillance and contact-tracing teams—gathered this week to demand months of unpaid wages. The protesters, carrying placards that read “No money, no data!” and “No payment for months,” represent a vital link in the containment chain that has now been severed. Biongi Beiza, one of the protesters, noted that many workers have received no compensation for their labor in August and September. Without these surveillance teams, health officials are essentially flying blind, unable to track the movement of the virus through the community or identify new clusters before they explode into localized epidemics.
The strike is not an isolated incident but rather the latest in a series of labor disputes that have plagued the response effort since its inception. Front-line workers, who risk their lives daily by coming into contact with one of the most infectious substances on earth, have repeatedly expressed frustration over the government’s failure to provide the financial support promised to them. The Congolese administration has yet to provide a comprehensive explanation for the payroll failures, leaving a vacuum of leadership that further demoralizes a workforce already exhausted by the physical and emotional toll of the outbreak.
Compounding the labor crisis is a deteriorating security environment that has seen the direct targeting of medical facilities. A senior official from the United Nations reported a catastrophic incident earlier this week in Kigonze, on the outskirts of Bunia. Soldiers reportedly burned a displacement camp that housed a transit center for Ebola patients. The military action, which was purportedly an attempt to search for hidden weapons, forced an estimated 19,000 internally displaced persons (IDPs) to flee. The destruction of the transit center is a massive blow to the regional response. Julien Harneis, the U.N. senior Ebola coordinator, emphasized that every time a center is lost, years of investment and critical care capacity vanish. In a region where medical resources are already spread thin, the loss of a facility means that infected individuals are forced back into the community, where they are likely to transmit the virus to family members and neighbors, or die without the dignity of medical supervision.
The human cost of this insecurity is staggering. The displacement of 19,000 people from the Kigonze camp creates a nightmare for epidemiologists. When large groups of people move suddenly and without oversight, the ability to monitor "contacts"—those who have been exposed to the virus—becomes nearly impossible. This movement acts as a catalyst for the virus to jump into new, previously unaffected "health zones," a trend that has the World Health Organization (WHO) on high alert. The WHO has warned that if the current trajectory continues, this outbreak could eventually rival the scale of the 2014-2016 West African epidemic, which claimed more than 11,000 lives across Guinea, Liberia, and Sierra Leone.
The international community has also been directly affected by the escalating risks. Médecins Sans Frontières (MSF), or Doctors Without Borders, confirmed that one of its aid workers contracted the virus while operating in the DRC. The infected staff member was evacuated to the Netherlands via a high-security medical flight and is currently being treated in a specialized isolation unit at the Leiden University Medical Center. This case highlights the extreme danger faced by those on the front lines; to date, at least 50 health workers have died after contracting Ebola during this outbreak. MSF has described the human cost in the DRC as "unprecedented," noting that the combination of a high-fatality disease and a regional conflict has created a humanitarian emergency of the highest order.
Despite these setbacks, there have been pockets of technological success. Local authorities have increasingly relied on mobile laboratories to bridge the gap between diagnosis and treatment. In cities like Butembo, medical teams are now utilizing these labs to slash the time required for testing. Previously, it could take up to 72 hours for a blood sample to be transported to a central lab and processed. With mobile units, that window has been reduced to just six hours. Dr. Lota Kalubi, who works at a treatment center in Butembo, noted that rapid testing is the difference between life and death. If a patient can be confirmed positive within hours, they can be isolated immediately, and their family members can receive the Ebola vaccine as part of a "ring vaccination" strategy. Michel Ngimba of the National Institute of Biomedical Research added that the mobility of these labs allows the response to be "agile," moving equipment into remote or newly emerging hotspots like Katwa at a moment’s notice.
However, technology can only do so much in the face of profound community resistance. The Eastern DRC is a region defined by decades of conflict, marginalized by the central government in Kinshasa, and suspicious of outside intervention. Many residents view the Ebola response through a lens of political skepticism. In some areas, the virus is dismissed as a "hoax" or a conspiracy designed to generate funding for NGOs or to manipulate election outcomes. This mistrust turned deadly earlier this week when a Congolese politician was beaten to death by a mob after he attempted to defend the government’s Ebola containment measures. Such acts of violence underscore the "community gap" that remains the biggest hurdle for health officials.
In response to this resistance, authorities launched a "village-centered approach" last month. This strategy involves pivoting away from large, intimidating treatment centers run by foreigners and instead working through local leaders, elders, and traditional healers to educate the public. The goal is to humanize the response and integrate it into the existing social fabric of the villages. Yet, this approach is being tested by the persistent lack of security. In areas where armed militias operate, health workers cannot enter without military escorts, and the presence of soldiers often further alienates the local population, creating a vicious cycle of fear and avoidance.
Data from the Africa Centers for Disease Control and Prevention (Africa CDC) provides a nuanced view of the outbreak’s current state. While the overall number of newly confirmed cases has shown a slight decline—dropping from an average of 850 cases per week in July to roughly 490 in September—experts warn against complacency. The drop in numbers may not reflect a true slowing of the virus but rather a decrease in the ability of health teams to find and report cases due to the strikes and insecurity. While the disease appears to be slowing in some traditional hotspots, it is accelerating in new zones where the infrastructure is even less prepared to handle an influx of patients.
The 2018-2019 Ebola outbreak in the DRC is occurring in a "perfect storm" of conditions: a highly dense population, a mobile and displaced citizenry, a history of political instability, and a region plagued by active warfare. The milestone of 4,000 deaths is a grim reminder that without a stabilization of the security situation and a resolution to the labor disputes, the virus will continue to outpace the efforts to stop it. The international community, including the Gates Foundation which provides financial support for health coverage in the region, continues to monitor the situation, but the consensus among experts is clear: the fight against Ebola in the DRC is as much a battle for hearts, minds, and peace as it is a battle for medical recovery. As the surveillance teams in Bunia continue their strike, the world waits to see if the "no money, no data" stalemate will break before the virus finds its next 4,000 victims.
